

























































Obesity Medicine

Latest News


CME Content


In patients with underlying disease, a preoperative evaluation and targeted perioperative management strategies can minimize surgical complications and maximize healing. This article focuses on how to identify surgery patients at risk for complications caused by diabetes, chronic obstructive pulmonary disease (COPD), and other medical conditions; I also describe strategies to minimize such risk.
Abstract: The coexistence of asthma and obstructive sleep apnea (OSA) in a given patient presents a number of diagnostic and treatment challenges. Although the relationship between these 2 diseases is complex, it is clear that risk factors such as obesity, rhinosinusitis, and gastroesophageal reflux disease (GERD) can complicate both asthma and OSA. In the evaluation of a patient with poorly controlled asthma, it is important to consider the possibility of OSA. The most obvious clues are daytime sleepiness and snoring, but the definitive diagnosis is made by polysomnography. Management of OSA may include weight loss and continuous positive airway pressure (CPAP). Surgical intervention, such as uvulopalatopharyngoplasty, may be an option for patients who cannot tolerate CPAP. Management may include specific therapies directed at GERD or upper airway disease as well as modification of the patient's asthma regimen. (J Respir Dis. 2005;26(10):423-435)

The metabolic syndrome represents a clustering of conditions and/or risk factors that lead to an increased incidence of type 2 diabetes mellitus and cardiovascular disease. These conditions include abdominal obesity, dyslipidemia, hypertension, insulin resistance, and a proinflammatory state.

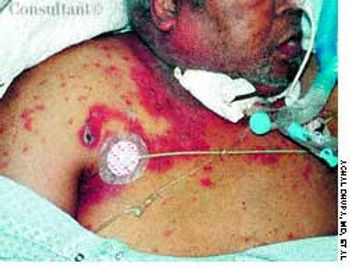
A 72-year-old morbidly obese man who had diabetes mellitus was admitted to the hospital from a nursing home with a fever of 4 days' duration. A tracheostomy had been performed 3 months earlier for respiratory failure. The patient was being treated with corticosteroids for chronic obstructive pulmonary disease.

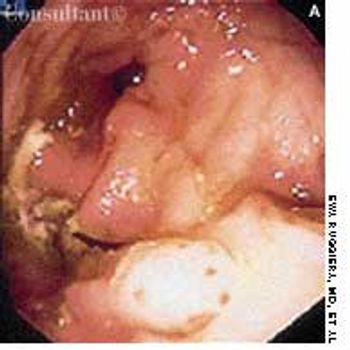
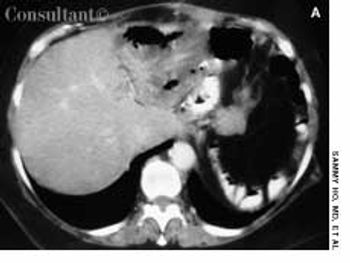
A 45-year-old man presented with a 2-month history of progressive fatigue, weight loss of 10 lb, abdominal pain, and pruritus. The patient had been taking a maintenance dose of oral mesalamine since he received a diagnosis of ulcerative colitis 14 years before.

A 71-year-old man, who had recently returned from a month in Europe, complained of left lower leg swelling and pain of 1-week's duration. For many years, this obese patient had chronic venous insufficiency of both legs and chronic osteoarthritis of the knees that severely limited his ability to walk. The patient was admitted to the hospital with extensive cellulitis of the left lower leg.

A 49-year-old woman, severely obese but otherwise healthy, appeared for a preemployment medical examination. She neither smoked cigarettes nor drank alcohol. She had no respiratory problems and recalled no family history of such. A baseline mammogram taken 4 years earlier showed no abnormalities, and the patient was not under care for any medical condition. Results of physical examination were normal, except for the obesity-which made it difficult to determine breast masses with confidence.

Zinc Deficiency

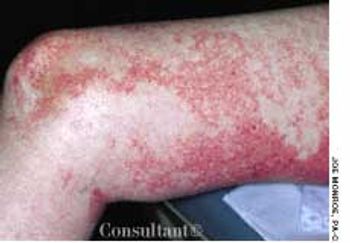
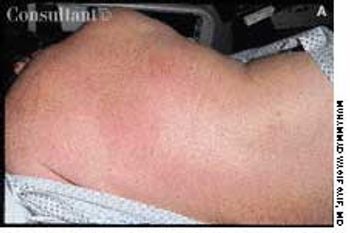
A 44-year-old woman had a painful, burning rash for 4 months. The erythematous eruption was evident on the thighs, fingers, buttocks, abdomen, and perineal and intergluteal areas. Application of triamcinolone cream and emollients offered no relief.

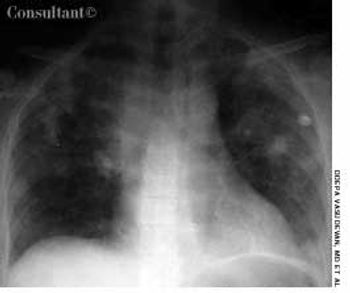
Over the past 6 months, a 72-year-old man was troubled by a persistent cough; he also had lost 9 kg (20 lb). He had no fever or chills, but he noticed mild streaking of blood in his sputum during the past month. He had been a cigarette smoker for 50 years.

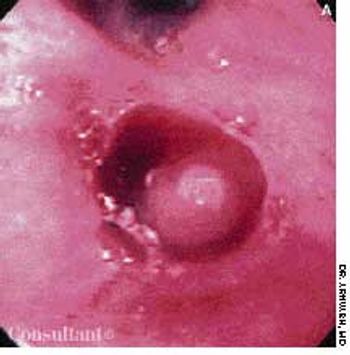
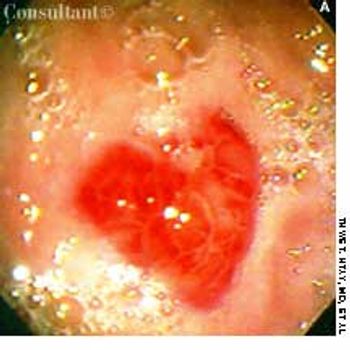
Three weeks after undergoing gastric bypass surgery for obesity, a 64-year-old woman presented with fatigue, chills, and abdominal pain of 2 days' duration. She denied shortness of breath, nausea, vomiting, changes in bowel habits, melena, and hematochezia. The patient had no significant past medical history.

A 32-year-old man presented with a yellow, papular rash on the buttocks and extensor surfaces. His medical history included diabetes mellitus, alcoholism, obesity, and polysubstance abuse. Laboratory results disclosed a serum triglyceride level of 5,793 mg/dL.

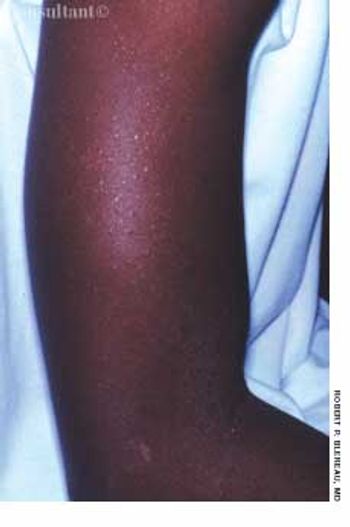
For 2 months, an asymptomatic rash had been present on the upper arms of a 16-year-old boy of normal weight. The rash, as seen on the patient's right arm, consisted of abundant fine papules. He had no other lesions.

A 16-year-old African American boy complained of exertional pain below his left knee that severely limited his ability to participate in sports. The patient had had bilateral bowed legs until his early school years, when the right knee straightened. For the past year, exertional pain had been present below the left knee in the epiphyseal area.

HIV infection was diagnosed in a 34-year-old man 3 years before he was hospitalized. The patient had a 2-week history of nausea; vomiting; and diffuse, intermittent, poorly localized abdominal pain. He had received radiotherapy and chemotherapy for Kaposi's sarcoma (KS) of the upper and lower extremities, which had been diagnosed 8 months earlier.

A 27-year-old man from Iraq presented with a painful lesion on the left lateral aspect of his tongue of 2 weeks' duration. Genital ulcers or skin lesions were not present. The patient also complained of a low-grade fever, weight loss, and occasional episodes of left eye pain during the past several months. He denied any significant past medical history, allergies, and the use of medications or illicit drugs.

For 1 month, a 25-year-old woman had experienced discomfort in and around the left eye and diplopia. She was in good health; she reported no weight loss, excessive nervousness, heat intolerance, decreased strength, changes in the texture of hair or skin, or altered bowel habits. There was no personal or family history of goiter or other thyroid disease.

After 5 weeks of undulating fever, weight loss, and night sweats, a 22-year-old man presented to the emergency department. He reported no significant medical history. The patient had recently completed a course of tetracycline followed by another of azithromycin for a presumed upper respiratory tract infection.

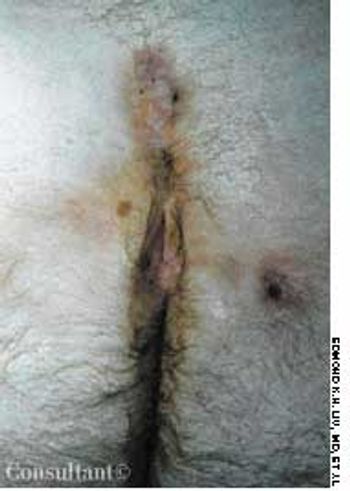
A 45-year-old man sought medical advice after suffering for 6 months with recurrent pain and a purulent discharge at the sacrococcygeal region. Two weeks before this consultation, an abscess on the patient's right buttock had been drained by another physician. The patient had insulin-dependent diabetes mellitus for 5 years; his medical history was otherwise unremarkable.