All News

True Polydactyly

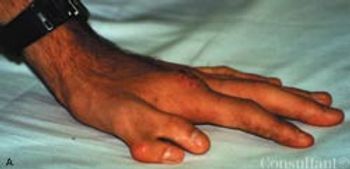
Two patients who presented for evaluation of unrelated maladies were noted to have true polydactyly. Both patients-a 32-year-old white man and a 35-year-old African American woman - had a duplicate left thumb. There were no other associated congenital abnormalities.

Epigastric Hernia

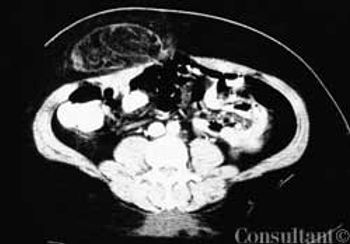
A 48-year-old woman complained of dull, aching abdominal pain and epigastric swelling. She had a 6- to 7-month history of painless swelling that intermittently decreased in size. The patient denied vomiting and nausea.

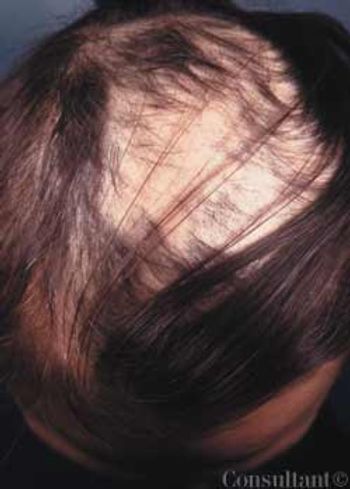
Bald patches were noted on the head of a 40-year-old woman with longstanding mental illness. She claimed, “I have to pull out my hair, so my scalp won’t hurt.” The patient began pulling out her hair when she stopped taking her psychotropic medications 6 years earlier.

A 12-year-old African American girl comes to youroffice for a well-child checkup. She is tall for herage (height above the 95th percentile) and obese(body mass index [BMI] above the 95th percentile).Physical examination reveals acanthosisnigricans on her neck, axilla, and upper abdominalregion (Figure) and a vaginal yeast infection.Routine urinalysis reveals a glucose level ofgreater than 1000 mg/dL, with negative proteinand ketones. A random blood glucose test, obtainedbecause of the glucosuria, is 249 mg/dL.

A 31-year-old man presents with a2-week history of a constant, dull acheand hearing loss in the right ear. Healso complains of intermittent sharppains that are usually followed bydrainage through the external auditorycanal. Another practitioner diagnosedacute otitis media with tympanic membraneperforation, for which he prescribeda 10-day course of amoxicillin.The patient completed the regimen buthas obtained no relief.

ABSTRACT: Fibromyalgia syndrome (FMS) is a common condition that causes chronic pain and disability. It should be diagnosed by its own clinical characteristics of widespread musculoskeletal pain and multiple tender points. American College of Rheumatology criteria guidelines are most helpful in diagnosing FMS. The major symptoms are pain, stiffness, fatigue, poor sleep, and those of other associated conditions, for example, irritable bowel syndrome, headaches, restless legs syndrome, chronic fatigue syndrome, and depression. The pathophysiology of FMS is thought to involve central sensitization and neuroendocrine aberrations, triggered or aggravated by genetic predisposition; trauma; psychosocial distress; sleep deprivation; and peripheral nociception.

Emphysematous Pyelitis

An obese 55-year-old woman had intermittent dysuria and frequent urination for 4 days and fever, abdominal pain, and vomiting for 3 days. Her history included type 1 diabetes mellitus, hypertension, and angina; her medications included insulin, nifedipine, and nitroglycerin.

Many of my patients are confused. So aremany of my colleagues. Official bodies ofexperts barrage the media with pronouncementson what constitutes goodpreventive medicine: screening tests, eatingor abjuring certain foods, avoidance of exposures tosun or environmental hazards, "correct" behaviors. Althoughthey acknowledge that the data are, and alwayswill be, imperfect, these experts try their best to directpeople in the way that the evidence points-for now.

Reiter Syndrome

Reiter Syndrome (also called reactive arthritis) manifests as peripheral arthritis that is sometimes accompanied by such extra-articular findings as urethritis, conjunctivitis, and uveitis

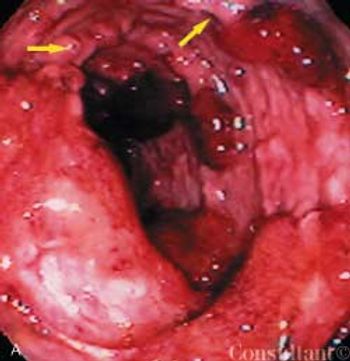
For 6 weeks, a 29-year-old previously healthy man had between 10 and 15 episodes daily of small-volume bloody diarrhea with intermittent paraumbilical pain. Anorexia and the loss of 25 lb accompanied the diarrhea. The patient had no significant medical history, took no medications, had not traveled recently, and had no contact with sick persons. He denied fever, chills, nausea, vomiting, and all other symptoms.

The manifestations of this multisystemdisorder range from relativelybenign, self-limited cutaneous involvementto severe, potentially fatal systemicillness. Skin lesions associatedwith lupus erythematosus (LE) areclassified histologically as LE-specificor LE-nonspecific.

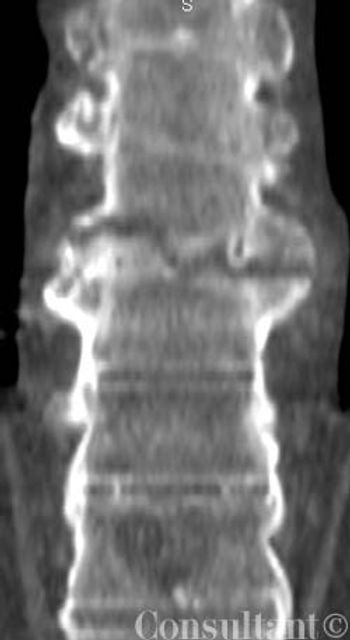
Twenty-four hours after a car accident, a 47-year-old man with chronic low back pain-which had been diagnosed years earlier as "arthritis" of the spine-presented with back and chest pain and requested an opioid analgesic. The patient had a history of alcoholism and illicit drug use. Tenderness of the thoracic area was noted.

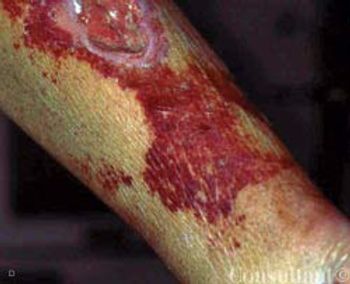
A 59-year-old man, who was unable to walk, was brought to the emergency department with severe leg pain, worsening weakness, increasing fatigue, chills, and fever of 3 days' duration. The symptoms began after a round of golf. In addition to the leg pain, which particularly affected the calf muscles, the lower extremities were red and swollen.

Low Back Pain

ABSTRACT: Regardless of the specific underlying pathology, most patients with low back pain benefit from a program of rehabilitative exercise. The goal of such a program is to increase muscle activity while minimizing stress to the spine. Low-intensity, high-frequency endurance training accomplishes both objectives. Include in the program flexibility exercises, exercises to strengthen the abdominal muscles, exercises for the proximal paraspinal and periscapular muscles, extensor exercises, and exercises to strengthen the legs and stabilize the trunk. Introduce the exercises in this order and advise patients not to progress to a new exercise until they are comfortable performing the less difficult ones.

Low Back Pain:

ABSTRACT: When a patient presents with low back pain, ask about the location and quality of the pain, what makes the pain increase or decrease, associated symptoms, and risk factors. Clues to systemic causes of low back pain include fever; arthritis; iritis; signs and/or symptoms of GI disease, pelvic disease, or renal disease; tachycardia; and integumentary abnormalities. Perform a neurovascular evaluation as well as a detailed musculoskeletal examination. Imaging studies are not necessary for most patients initially. Acute therapy consists of the application of cold and heat and analgesics such as acetaminophen or an NSAID. Early exercise-not bed rest-is the cornerstone of treatment. Follow-up is mandatory: in 3 to 7 days for patients with severe pain, inconsistent findings, mild neurologic abnormalities, or a history of progres- sive symptoms; and in 10 to 14 days for patients with no neurologic compromise.

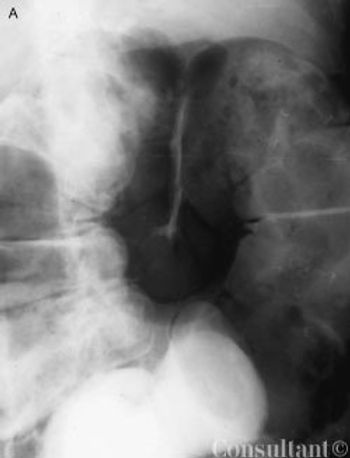
Progressive abdominal distention, nausea, constipation, and mild abdominal pain developed in an 82-year-old woman 5 days after she underwent surgical repair of a left hip fracture. Her medical history was significant for Parkinson disease, type 2 diabetes mellitus, and hypertension.

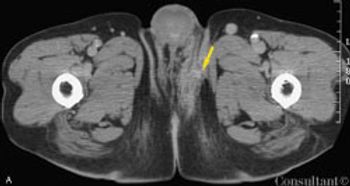
A 77-year-old African American man with type 2 diabetes mellitus and coronary artery disease presented to the emergency department with acute scrotal swelling and pain. His testicles were erythematous with focal areas of necrosis and associated tissue destruction. Similar skin changes were apparent in the lower abdominal and inguinal regions.

A 45-year-old woman presents with multiple injuries she sustained during a skiingaccident. She has fractures of her right arm and 3 ribs, as well as numerouscontusions. An abdominal CT scan shows no hemorrhage or other traumarelatedfindings; however, a 6.7-cm left adrenal mass is detected.