

























































































































Obesity Medicine

Latest News


CME Content


The prevention of symptomaticcoronary heart diseaseand other vascular disordersrepresents a significanthealth care priority, especiallyin a population that is growingolder and more obese. However,a recent survey has shownthat many laypersons-and evensome physicians-do not know allthe target lipid levels that are associatedwith optimal reduction ofcardiovascular risk.
ABSTRACT: A 4-pronged approach that includes patient education, skin and nail care, appropriate footwear, and proactive surgeries can effectively prevent diabetic foot problems. Teach patients with diabetes to examine their feet daily to detect new onset of redness, swelling, breaks in the integrity of the skin, blisters, calluses, and macerated areas. Have them follow a daily foot care regimen that includes warm water soaks and lubrication, and have them keep toenails properly trimmed. Recommend that patients select shoes that fit properly and have sufficient padding and toe box space; have them use inserts, lifts, orthoses, or braces--as recommended-to correct abnormal gait patterns. Finally, if deformities develop, simple proactive surgical procedures can correct these problems before they result in the development of wounds.

ABSTRACT: In patients with jaundice and normal liver function, the cause of hyperbilirubinemia is an isolated disorder of bilirubin metabolism. In patients with hyperbilirubinemia who have abnormal liver enzyme levels, hepatocellular disease must be differentiated from cholestatic liver injury. In general, if the cause of jaundice is global hepatocellular dysfunction, the serum alanine aminotransferase and aspartate aminotransferase levels will be predominantly elevated. If the cause is cholestasis, the serum alkaline phosphatase and gγ-glutamyl peptidase levels will be elevated. In most patients, imaging studies will be needed. The initial workup should include abdominal ultrasonography, which can identify dilated intrahepatic and extrahepatic biliary ducts as well as findings that may suggest cirrhosis or signs of portal hypertension, including splenomegaly and ascites.

WALTHAM, Mass. -- Pulse pressure, the difference between systolic and diastolic pressures, may be a risk factor for the onset of atrial fibrillation independent of arterial pressure and other known factors, researchers said.

WINSTON-SALEM, N.C. -- If patients are overweight or obese when they reach age 70, matters will probably get worse over the next decade, when aging bodies gain fat and lose lean mass in these vulnerable years, researchers reported.

Declining cardiovascular function, poor circulation, diabetes, obesity, cancer, immunodeficiency, renal disease, and thinned, xerotic skin provide the setting for a host of bacterial infections in elderly persons that can involve any level or structure of the skin.

A 49-year-old white man, in whom HIV infection had been newly diagnosed (CD4+ cell count, 25/µL; HIV-1 RNA level, 274,000 copies/mL), was transferred to our hospital for further workup and treatment of multiple neurologic deficits. He had presented to another hospital with a 4-day history of left-sided weakness and numbness, left-sided facial droop, dysphonia, and dysphagia that led to the initial diagnosis of an acute stroke.

A 75-year-old woman had undergone a total thyroidectomy, with histologic evidence of poorly differentiated follicular thyroid cancer. She subsequently received an ablative dose of iodine-131. After a disease-free interval of about 2 years, she presented with evidence of recurrence in the thyroid bed. She had enlarged cervical lymph nodes and complained of dyspnea on exertion.

A 69-year-old man with a history of atrial fibrillation, pulmonary embolism, asthma, and obstructive sleep apnea presented to the emergency department for evaluation of dyspnea and light-headedness. He had been treated for paroxysmal atrial fibrillation over the past 5 years; fairly good control had been achieved with metoprolol and amiodarone. However, over the past several months, he had been experiencing intermittent episodes of atrial fibrillation.

ABSTRACT: Angiotensin-converting enzyme (ACE) inhibitor therapy is recommended for all patients with heart failure (HF) and a reduced ejection fraction. It is generally initiated in the hospital at low doses as inotropic therapy is tapered. Angiotensin II receptor blockers may be a suitable alternative for patients who cannot tolerate ACE inhibitors. For patients who cannot tolerate either class of drug, a combination of hydralazine and a nitrate is recommended. ß-Blockers are first-line therapy for patients with current or previous symptoms of HF and reduced left ventricular function, as well as all patients hospitalized for HF. An aldosterone antagonist may be added to the regimen of patients with moderately severe to severe symptoms and reduced ejection fraction whose renal function and potassium concentration can be monitored.

ABSTRACT: Heel pain that occurs with the first several steps in the morning and diminishes as walking continues is the classic symptom of plantar fasciitis. Assessment of risk factors, such as improper footwear, a change in physical activities, and a new running surface, is important. Radiographs are rarely useful. Plantar fasciitis is generally self-limited; symptoms typically take 6 to 18 months to resolve. Conservative measures may include relative rest, stretching, strengthening, shoe modifications, orthoses, night splints, NSAIDs, and ice therapy. A corticosteroid injection may be warranted in resistant cases. If extensive conservative treatment is unsuccessful, referral to an orthopedic surgeon may be indicated.

A 48-year-old woman is evaluated for transfer to the ICU. She presented to the emergency department 48 hours ago with severe abdominal pain and emesis. The pain had started several days earlier and was located in the upper abdomen with some radiation to the back. No position--even the fetal position--provided relief. After admission, she was given intravenous fluids and analgesics; in the last several hours, her condition has deteriorated. She now complains of thirst and is somewhat agitated.

For a week, a 39-year-old woman with a history of intravenous heroin use had generalized pain, fever, chills, and a nonproductive cough. She rated the pain at 10 on a scale of 1 to 10; it was sharp, constant, and unrelieved by heroin. She also reported dyspnea at rest, pleuritic chest pain, and a 15-lb weight loss over the past month. She had no significant medical history or drug allergies, smoked a half pack of cigarettes per day, and denied alcohol use.

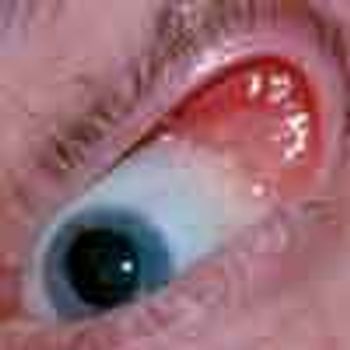
Floppy Eyelid Syndrome

For several days, the left eye and eyelids of a 60-year-old obese man had been red and irritated. The symptoms were worse in the morning after waking. The patient had recently started wearing a nighttime continuous positive airway pressure mask for obstructive sleep apnea (OSA). He slept exclusively on his left side.