All News

Lymphedema Tarda

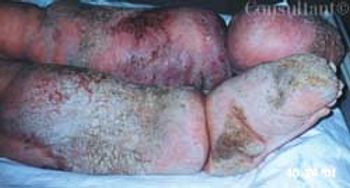
A 40-year-old man presented with a 5-year history of progressively increasing bilateral leg swelling that was neither painful nor pruritic. There was no history of dyspnea, jaundice, or groin surgery. The patient reported multiple previous episodes of superimposed cellulitis, which were treated with antibiotics. There was no family history of similar illness.

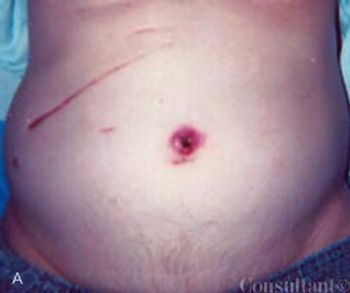
An 85-year-old man presented with intermittent abdominal pain of several years’ duration. Two years earlier, he underwent a laparoscopic cholecystectomy that was converted to an open procedure.

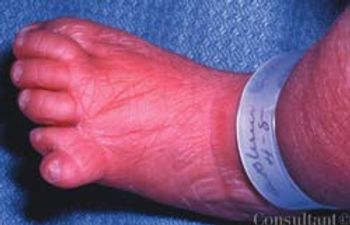
Polysyndactyly

This 2-day-old infant was noted by Robert P. Blereau, MD, of Morgan City, La, to have duplication of the fifth toe with webbing between the two toes to the distal interphalangeal joint. There was a family history of polydactyly on the paternal side and syndactyly on the maternal side.

ABSTRACT: In addition to advanced age, factors such as comorbid illness and debility determine the risk of community- acquired pneumonia (CAP). Many elderly persons do not have the classic symptoms of CAP; instead, they may present with confusion, lethargy, tachypnea, anorexia, or abdominal pain. Even with thorough investigation, an infectious pathogen can be identified in only about half of patients. In addition to the causative organisms for pneumonia in younger adults, elderly persons are at risk for infection with organisms such as Haemophilus influenzae, Staphylococcus aureus, enteric gram-negative bacteria, and anaerobes, and for polymicrobial infection. Prompt empiric treatment is essential. Recommended initial therapy choices include a ß-lactam agent with a macrolide, or an antipneumococcal fluoroquinolone.

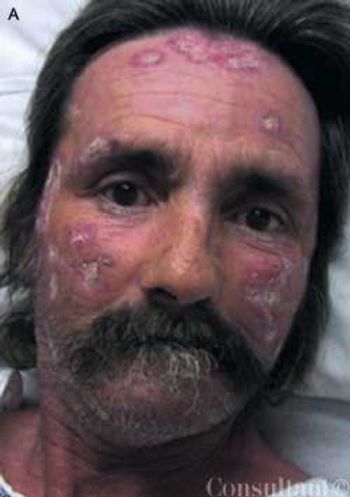
Bullae had recently appeared on the dorsa of the hands and fingers of a 46-year-old man. His medical history was significant for alcoholism, discoid lupus erythematosus (DLE), and hepatitis C. Systemic lupus erythematosus (SLE) was ruled out; the patient’s symptoms did not meet the American Rheumatism Association criteria for SLE.

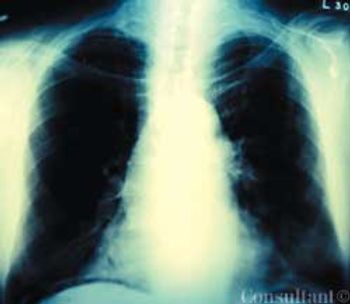
A 75-year-old man was brought to the emergency department with fever, cough, and abdominal pain of 2 days’ duration. The pain was most severe in the epigastric and umbilical regions. The patient’s history included type 2 diabetes mellitus, hypertension, and hypercholesterolemia. He had smoked cigarettes for 40 years and recently lost 50 lb. The patient was tachypneic and diaphoretic.

The Geriatric Depression Scale is the most widelyvalidated screening tool. The questionnaire has beenreduced to a single question that is as sensitive and as specificas the 15-item shortened form of the original 30-itemscale. The question is: "How often do you feel sad or depressed?'This is certainly something that is easy to ask inthe course of a general physical examination or routine officevisit.

Infant Colic:

ABSTRACT: Infant colic is a diagnosis of exclusion; its true cause is not known. To rule out alternative diagnoses, obtain a detailed history, look for clues to an underlying organic disease or genetic syndrome, and perform regular head-to-toe physical examinations. The interventions most commonly used to treat colic include modification of parental behavior (such as increased carrying of the infant or decreased infant stimulation), milk- and/or soy-free formulas, modifications in the diet of a breast-feeding mother, soothing measures (such as car rides, rocking, or use of a pacifier), anticholinergic agents, sedatives, and alternative medicine approaches (such as sucrose solution, herbal teas, or infant massage). The medications used to treat colic-such as antispasmodics and anticholinergics-can have serious adverse effects; discuss the pros and cons of drug therapy with parents before prescribing these agents. Remind parents that colic resolves by age 3 to 4 months, regardless of the intervention used.

A 12-month-old infant is brought to your office for evaluation of ared, swollen left index finger, which her parents first noted the prior evening.The mother denies any known trauma or recent illness. She tells you that theinfant is slightly fussy and is not taking her bottle as well as usual.

A 26-year-old woman complained of flatus and fecal incontinence of solid stool.One year earlier, she was delivered of a 3.86-kg (8.5-lb) infant; a severe perinealtear was repaired after the birth.

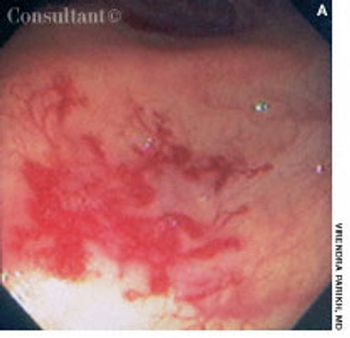
A 74-year-old man presented with generalized itching and mild jaundice. A year earlier, he had undergone a laparoscopic cholecystectomy.

Gardner Syndrome

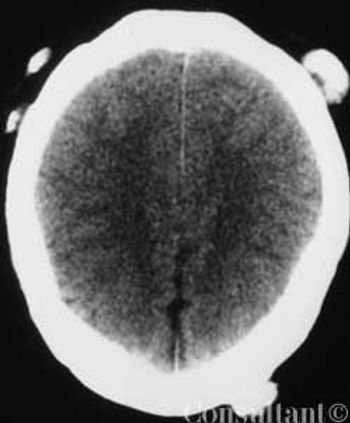
An otherwise healthy 38-year-old woman presented to the emergency department with a 1-day history of generalized left-sided weakness. She had no other significant medical history and was taking no medications. The patient was overweight.

Postcholecystectomy

A 74-year-old man presented withgeneralized itching and mild jaundice.A year earlier, he had undergone alaparoscopic cholecystectomy.

Persons with severe mental illnesses (SMI), such as schizophrenia, are at increased risk for comorbid conditions- including type 2 diabetes-independent of therapy. SMI sufferers especially at risk for type 2 diabetes are women, African Americans, and persons older than 45 years. Among the possible causes of increased susceptibility to type 2 diabetes are such schizophrenia-associated conditions as impaired glucose tolerance, overweight, obesity, inadequate nutrition, lack of exercise, and inadequate self-care. Other obstacles to good health care among patients with schizophrenia include impaired communication ability, denial of illness, social withdrawal, and undertreatment because of comorbid conditions. Different antipsychotic medications may also contribute to preexisting insulin resistance or glucose intolerance. Clinicians can optimize care by understanding the most significant barriers for each patient and incorporating this knowledge into an active treatment plan.

Drs Gary Quick, Theodore Ruff, and Pam Wilson’s “What’s Wrong With ThisPicture?” case of a woman with splenic laceration resulting from an assault by amale friend (CONSULTANT, May 2002, page 714) seems to have missed the“elephant in the living room.”

A nondrug remedy for menstrual discomfortis to apply a heating pad tothe lower abdomen when symptomsbegin.

For patients with a persistent coughwho cannot take codeine, a combinationof benzonatate (1 or 2 100-mgcapsules tid prn), along with dextromethorphanand guaifenesin (2 or3 tsp tid prn), can be effective.