































































































































Reducing hyperglycemia in older patients with chronic kidney disease may be best accomplished using incretin-based agents.
Reducing hyperglycemia in older patients with chronic kidney disease may be best accomplished using incretin-based agents.
Short-term sleep deprivation reduces insulin sensitivity in peripheral tissue, including fat cells, possibly leading to type 2 diabetes mellitus or obesity.
What is known about diabetes mellitus in older adults, how DM affects them differently than younger adults, what can be done to prevent or manage the disease, and how best to fill critical gaps in the evidence to address older patients’ needs.
High to middle levels of physical activity are associated with a lower risk of mortality in patients who have diabetes mellitus, according to a recent study.
More than half of adults 65 years and older have at least 3 chronic conditions, such as heart disease, diabetes mellitus, arthritis, high blood pressure, and Alzheimer disease, according to the American Geriatrics Society.

Persistent hyperglycemia despite triple oral antidiabetic therapy requires reassessment of medications with particular attention to risks for weight gain and hypoglycemia.

Hyperglycemia uncontrolled by oral antidiabetes agents alone can be complicated by drug-induced weight gain. GLP-1 agonists and DPP-4 inhibitors offer alternatives.
The addition of basal insulin to current oral medication is the simplest way to initiate insulin therapy in patients with type 2 diabetes.
Hypertension is very common in people with diabetes; in this patient’s case, it may have been present for 5 to 10 years before the hyperglycemia appeared.

In addition to lifestyle changes, how would you treat this patient?

Up to 80% of those with necrobiosis lipoidica have diabetes mellitus; however, this disorder develops in fewer than 1% of people who have diabetes.

Early use of combination therapy to treat type 2 diabetes is shown to limit glucose toxicity and preserve beta-cell function.
Despite best efforts with lifestyle modification and adherence to metformin and glimepiride therapy, this man’s A1C continues to rise. What next?

Achieving sustained reductions of hyperlipidemia and blood pressure in a patient with diabetes is not impossible, but it's a challenge. A new study comparing two health systems shows which factors increase the odds of success.
For many patients with diabetic peripheral neuropathy, severe pain can be controlled to a degree sufficient to improve their quality of life. Here: effective management strategies, including topical agents, oral medications, and nonpharmacological therapies (eg, acupuncture and transcutaneous nerve stimulation).
Blood sugar and HbA1C are very high; how would you treat this patient's hyperglycemia?

Type 2 diabetes mellitus is affecting teenagers at an alarming rate. Lifestyle changes are paramount in an environment of chronic caloric surplus.
Once-weekly exenatide, the recently approved GLP-1 receptor agonist, may help improve treatment adherence and outcomes in patients with type 2 diabetes.
The Outcomes Reduction with Initial Glargine Intervention trial: No elevated risk of cardiovascular disease, cancer when insulin is used early to treat T2DM.
The 2012 ADA/EASD Position Statement prescribes patient-centered care for type 2 diabetes management using lifestyle change, metformin, DPP-4Is, GLP-1 RAs.

This type 2 diabetes office-visit checklist tracks A1c, lipid, and blood pressure goals, and lets you monitor regular labs, exams, and diabetes education.
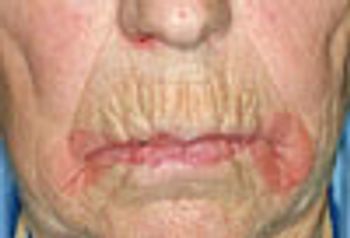
These burning red patches around the mouth, known as perleche, are aggravated by aging. Learn how to treat it.
New research finds that type 2 diabetes mellitus, once considered a disease of “adult onset,” is highly resistant to treatment in overweight American youths-a group succumbing to the disorder at an alarming rate. Here, a comment on the cultural norms that make choosing health a daily battle.
The elderly patient has had type 2 diabetes for 15 years is now home bound after a stroke. Her HbA1c is 9.6 and she takes only metformin. Review the rest of her laboratory results and propose a management plan.
Would you treat the elevated A1C aggressively-and what would your target level be? Would you consider statins? Dr Shahady invites your insights.