














































































A 50-year-old man was brought to the emergency department (ED) after a witnessed syncopal event. He was awake but confused and unable to provide a history.
A 50-year-old man was brought to the emergency department (ED) after a witnessed syncopal event. He was awake but confused and unable to provide a history.
A 72-year-old obese man with chronic atrial fibrillation, hypertension, hyperlipidemia, and a history of tobacco use presented for a routine office visit. A year earlier, he began to experience recurrent chest pain, but an ECG had shown normal T waves.
A previously healthy 55-year-old woman complained of fever, weakness, and generalized malaise for the past 3 to 4 weeks. She had been treated with ciprofloxacin, amoxicillin, and azithromycin for 21 days with no resolution of her symptoms. Five days before she was hospitalized, multiple nonspecific constitutional complaints developed.

Elective splenectomy has been scheduled for a 60-year-old man with severe idiopathic thrombocytopenic purpura (ITP) that has responded poorly to treatment. His current platelet count ranges from 5000/μL to 10,000/μL despite several months of aggressive therapy, including 2 courses of high-dose corticosteroids and 2 courses of intravenous immunoglobulin.
From the perspective of a harried primary care physician, it’s very difficult to sort out arguments and data when two respected specialists diametrically disagree.
A previously healthy 19-year-old woman presents with a sore throat that has become progressively more painful over the course of 1 week. She also has left-sided neck swelling, light-headedness, and intermittent headaches. She denies recent sexual activity.
A 23-year-old woman presents to the emergency department (ED) with left-sided burning chest pain that radiates to the epigastrium. The pain, which woke her from sleep 12 hours earlier, is intermittent and is not associated with eating or exertion. She had a single bout of nausea and emesis.
A new patient with a history of atrial fibrillation (AF) and heart failure presents for an initial visit. The 72-year-old man denies exertional chest pain and paroxysmal nocturnal dyspnea. He is able to perform all his routine daily activities and can even climb 2 flights of stairs without dyspnea-although with more vigorous effort, he does become short of breath. He occasionally experiences pedal edema at the end of the day, but the condition resolves by morning.
A 36-year-old woman presented to the emergency department with loss of vision in the right eye that had initially involved the peripheral field and progressed over 2 months to the central and nasal fields. During this period, she also had headaches, vomiting, and generalized weakness. She had had amenorrhea for 1 year.
Which antibiotics are most likely to cause a clinically significant drug interaction in elderly patients who are receiving warfarin?
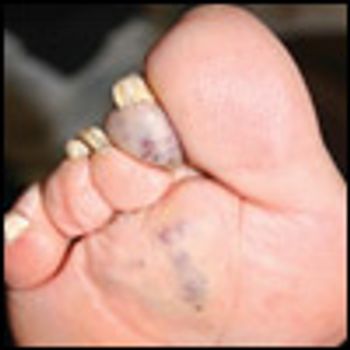
The plantar aspect of this toe shows purple nonuniform darkening that mimicked either a simple traumatic hematoma or the blue toe syndrome. More proximally, however, the solar aspect contained irregular dark-purple dots reminiscent of individual thrombosed venules, and in addition showed discontinuous purple zones more proximally in the part of the ray that lay within the body of the foot and that surely could not be imputed to any possible toe trauma or fracture nor to ischemia in the distribution of any single vessel. No purple area was warm or tender.
A 68-year-old African American man presents for a checkup. He has had type 2 diabetes mellitus for the past 5 years but has no nephropathy and no history of cardiovascular disease. He is currently taking atorvastatin, 80 mg/d, and his low-density lipoprotein cholesterol level is 80 mg/dL. His blood pressure was 148/98 mm Hg at the last visit and is now 150/98 mm Hg. What is the best treatment for him?
Because epidermal integrity decreases with age, eczematous inflammatory dermatoses are more common among older adults than among younger persons.
A 43-year-old white man presented to the emergency department with dyspnea, abdominal bloating, fever with chills, night sweats, decreased oral intake, and myalgia of 1 week's duration. He was found to have heart failure caused by systolic dysfunction. Viral myocarditis was the presumptive diagnosis after investigation for other causes.
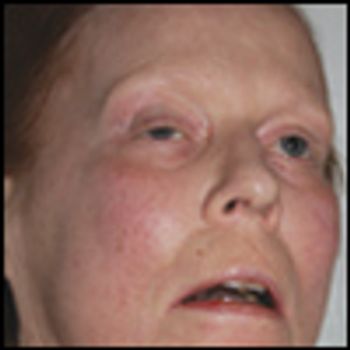
A 56-year-old woman seen during physician’s hospice visit. Stormy course from lupus nephritis, dialysisdependency, repeated episodes of dialysis-catheter–related peritonitis, each treated and followed by Clostridium difficile–associated disease.
Some women 75 and older who are in good health and have excellent functional status may benefit from mammography screening, while others who are in poor health and have short life expectancies probably do not.
Dr Rutecki makes some excellent points about the costs of diabetes care and how the reduction of complications such as myocardial infarction, heart failure, and renal disease will decrease costs and suffering. But I have difficulty with the tone of his comments that seem to shift blame for the cause of these costs.
A 68-year-old woman complains of diffuse, severe myalgia. She reports stiffness, heaviness, and cramping, which are most marked in her thighs and calves. The heaviness and discomfort result in a sensation of weakness as well.
American medicine is undergoing the greatest financial scrutiny in its history. The hue and cry for reform stems primarily from the soaring costs of health care. However, placing the blame for these costs solely on increased utilization of technology, cutting-edge pharmaceuticals, cost-shifting hospitals, and physicians misses a bigger mark.
A 74-year-old man with a history of diabetes mellitus, atrial fibrillation, and stroke had a stable, skin-colored mass on his upper back for the past 10 years that had suddenly become swollen and red.
A 62-year-old woman presents with epistaxis from the right nostril. Thenosebleed has lasted about 90 minutes, and she has become alarmedby the amount of blood on the tissues and washcloth she has applied to hernose.
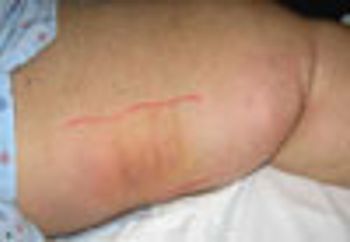
Up to 40% of patients who present with what may look like simple, isolated superficial venous thrombosis have concomitant deep venous thrombosis. This finding has led clinicians to first rule out DVT bilaterally via compression Doppler ultrasonography before treatment is considered.
A 92-year-old woman presented with signs and symptoms of heart failure, including marked bilateral lower extremity edema, jugular vein distention, and difficulty in breathing at rest. Her medical history was significant for hyperthyroidism, chronic asthmatic bronchitis, and senile dementia. Medications included oral methimazole, 10 mg/d, and oral theophylline, 200 mg/d.
What is the role of the primary care practitioner in the care of patients with HIV infection?Although the treatment of human immunodeficiency virus type 1 (HIV-1) infection is usually directed by subspecialists, many patients who are taking highly active antiretroviral therapy (HAART) continue to see their primary care physician. What is the most effective regimen-and what complications should we be on the lookout for?
Primary care physicians are called upon to assess risk in patients undergoing a variety of surgical procedures. In some ways, perioperative medicine is quickly evolving into a “subspecialty” of its own. Recently, Jaffer and associates1 updated the area with new data accumulated over the past 2 years.