














































































































































Telltale skin lesions of syphilis, gonorrhea, human papillomavirus infection, and Haemophilus ducreyi infection.

Telltale skin lesions of syphilis, gonorrhea, human papillomavirus infection, and Haemophilus ducreyi infection.
The authors describe the development of pneumonitis in a patient who had initially presented with edema of the lower extremities. Biopsy results supported the conclusion that the pneumonitis was caused by silicone injections the patient had received 5 years earlier.
The initial evaluation of a patient with community-acquired pneumonia (CAP) should include a careful search for comorbidities, according to a study by Falguera and associates.
Abstract: In addition to causing pulmonary disease, infection with Mycobacterium tuberculosis can result in a wide range of extrapulmonary manifestations, including abdominal involvement. Patients with acute tuberculous peritonitis typically present with fever, weight loss, night sweats, and abdominal pain and swelling. Intestinal tuberculosis is characterized by weight loss, anorexia, and abdominal pain (usually in the right lower quadrant). A palpable abdominal mass may be present. Patients with primary hepatic tuberculosis may have a hard, nodular liver or recurrent jaundice. The workup may involve tuberculin skin testing, imaging studies, fine-needle aspiration, colonoscopy, and peritoneal biopsy. Percutaneous liver biopsy and laparoscopy are the main methods of diagnosing primary hepatic tuberculosis. Treatment includes antituberculosis drug therapy and, in some cases, surgery. (J Respir Dis. 2005;26(11):485-488)
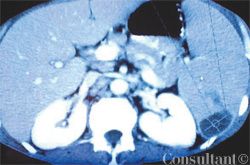
An HIV-positive 38-year-old man with a history of injection drug use presented to the emergency department with abdominal and back pain that worsened with motion. He denied fever and vomiting. During the past 2 months, the patient had been treated for a urinary tract infection (UTI) 4 times and evaluated for a renal calculus, which had been ruled out. He was currently receiving ciprofloxacin, ibuprofen, and HAART.
Telltale skin lesions of syphilis, gonorrhea, human papillomavirus infection, and Haemophilus ducreyi infection.
A 35-year-old man with type 1 diabetes has had an asymptomatic rash on the lower extremities for the past several months. He denies trauma and recent illness. He has tried multiple "home remedies," but the rash has persisted. He smokes and drinks alcoholic beverages occasionally.
Progressive cough and dyspnea of 2 months' duration prompted a 23-year-old man to seek medical attention for the fourth time. On previous emergency department visits, he had received antibiotics, which failed to relieve his symptoms.
A 36-year-old woman with a history of HIV disease presented for evaluation of dyspnea of 1 week's duration. She had been taking trimethoprim-sulfa- methoxazole for Pneumocystis carinii pneumonia prophylaxis. Because of a presumed skin reaction to this medication, dapsone was recently substituted.
A 24-year-old Korean woman, who was 20 weeks' pregnant, was referred to an allergist for an elimination diet and evaluation of the risk of allergies to her unborn child. She had a several-year history of perennial allergic rhinitis with seasonal exacerbations.
For patients with osteoarthritis, nonpharmacologic treatment can be an effective adjunct to drug therapy. Patient education is essential; both community-based and independent self-care programs are available. Weight loss can improve function and alleviate symptoms; however, it is more effective when dietary modification is accompanied by increased physical activity.
Statins (HMG-CoA reductase inhibitors) are the most effective drugs in the management of elevated low-density lipoprotein cholesterol (LDL-C) levels. Recent large clinical trials continue to demonstrate the remarkable efficacy of these agents, including improved outcomes.
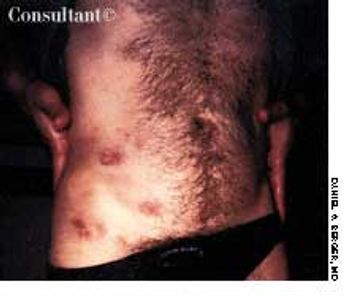
A 39-year-old man with HIV infection was being treated with antiretroviral therapy. He now sought help for multiple 2- to 3-cm violaceous papules on his right hip and the right lower abdominal area. A biopsy specimen showed intense, atypical lymphocytoid and monocytoid cells with prominent nucleoli, hyperchromatism, and bruised nuclei.
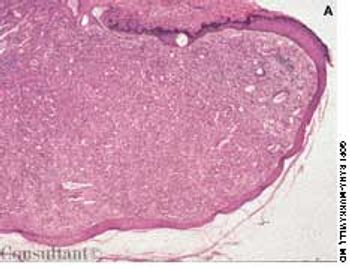
A 32-year-old construction worker sought evaluation of nontender skin lesions that had been erupting for several months. The patient was seropositive for HIV with a CD4+ cell count of 210/µL. He had no history of opportunistic infections.
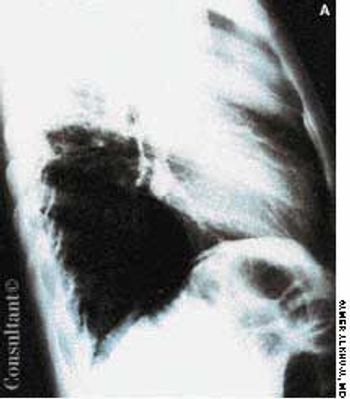
Except for a fever of 1 month's duration, a 28-year man had no other complaints. He said he used to smoke marijuana but never used intravenous drugs. His temperature was 39.4°C (103°F), but no other abnormalities were noted on physical examination.
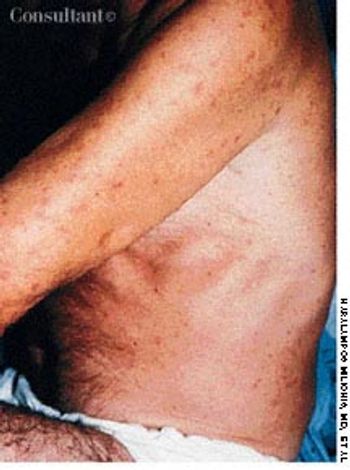
A 49-year-old farmer was hospitalized because of a 3-week history of intermittent fever, fatigue, anorexia, generalized myalgias, and malodorous sweating. A nonpruritic, nonhemorrhagic, maculopapular rash recently had developed on his arms, legs, and trunk. The reddish lesions were less than 1 cm in diameter. There was no history of antibiotic or antipyretic drug therapy, and no abnormalities were found on physical examination.

Ten days before presenting for evaluation, a 69-year-old man began to experience neuralgic pain and noticed the eruption of painful erythematous macules and papules on the right side of his chest. Within 24 to 72 hours, vesicles and pustules arose at the site. One week after onset, several of the lesions dried and crusted.
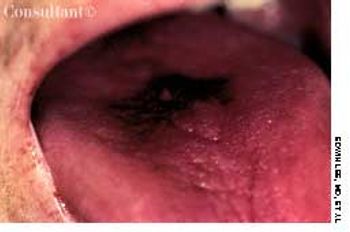
A 35-year-old HIV-positive man had a thick, black, otherwise asymptomatic patch on the top of his tongue. He did not have diabetes.
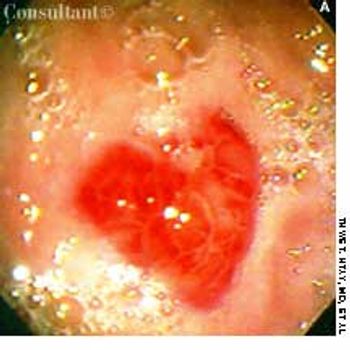
HIV infection was diagnosed in a 34-year-old man 3 years before he was hospitalized. The patient had a 2-week history of nausea; vomiting; and diffuse, intermittent, poorly localized abdominal pain. He had received radiotherapy and chemotherapy for Kaposi's sarcoma (KS) of the upper and lower extremities, which had been diagnosed 8 months earlier.
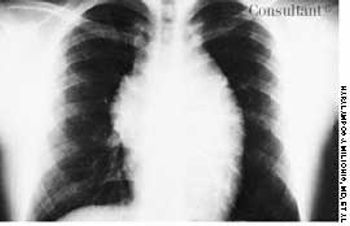
A 19-year-old man was admitted to the hospital with malaise, fatigue, and intermittent fever (temperature of 38°C [100.4°F]) for the last 2 weeks. Physical examination revealed scarce purpuric lesions over the lower extremities; a pericardial friction rub was audible over the precordium when the patient was supine and seated, and the spleen was remarkably enlarged.
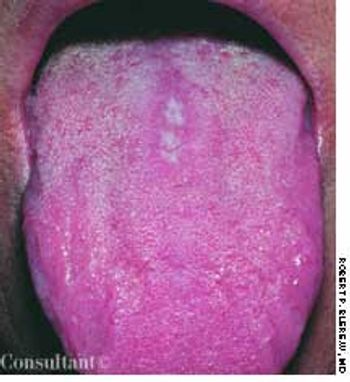
A 35-year-old woman complained of pain or a burning sensation on her tongue when she ingested hot or acidic food and beverages. The white patch had spontaneously developed on her tongue 3 months earlier.
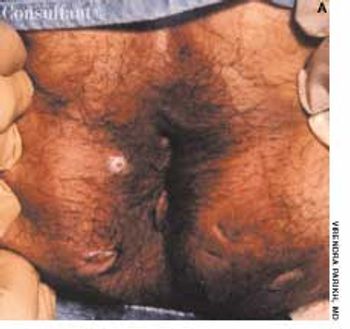
Fourteen months of intermittent, foul-smelling, perianal discharge prompted a 45-year-old man to seek medical evaluation. He also complained of occasional bright red rectal bleeding and soreness of the perianal region; he denied fever. The patient had undergone surgical drainage for episodes of perianal sepsis 2 years earlier.
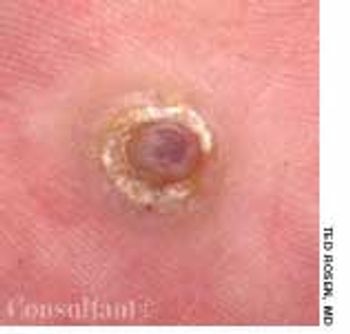
A 32-year-old man who was seropositive for HIV presented with a tender lesion on his right foot of about 3 months' duration. The patient's only medication was zidovudine. His CD4+ cell count was 120/μL.
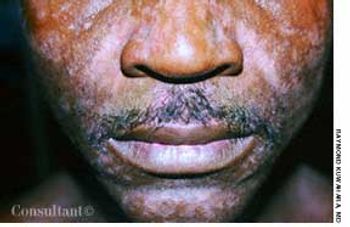
This 27-year-old man complained that a facial rash of several years' duration had worsened during the past few months. Hypopigmented macules with scale were especially prominent on the eyebrows and in the nasolabial folds; a moderate amount of scale was noted on the scalp. The patient was seropositive for HIV.
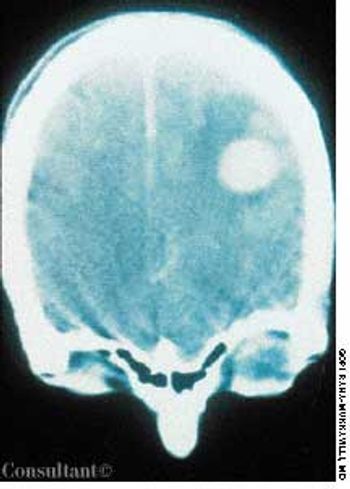
A 32-year-old man who had HIV disease complained of headache, fever, and weakness on his right side. His history included intravenous drug use, Pneumocystis carinii pneumonia, and mucocutaneous candidiasis.